Genetically engineered cell therapies for osteoarthritis are finally getting closer to patients. They are the ones with the real potential to eventually become the first Disease Modifying Drugs in OA (DMD).
Most of the work in regenerative medicine has focused on which cells we should use: bone marrow MSCs, adipose-derived cells, umbilical cells, chondrocytes, and others. But we can also genetically modify cells to enhance what they do once they are inside the joint.
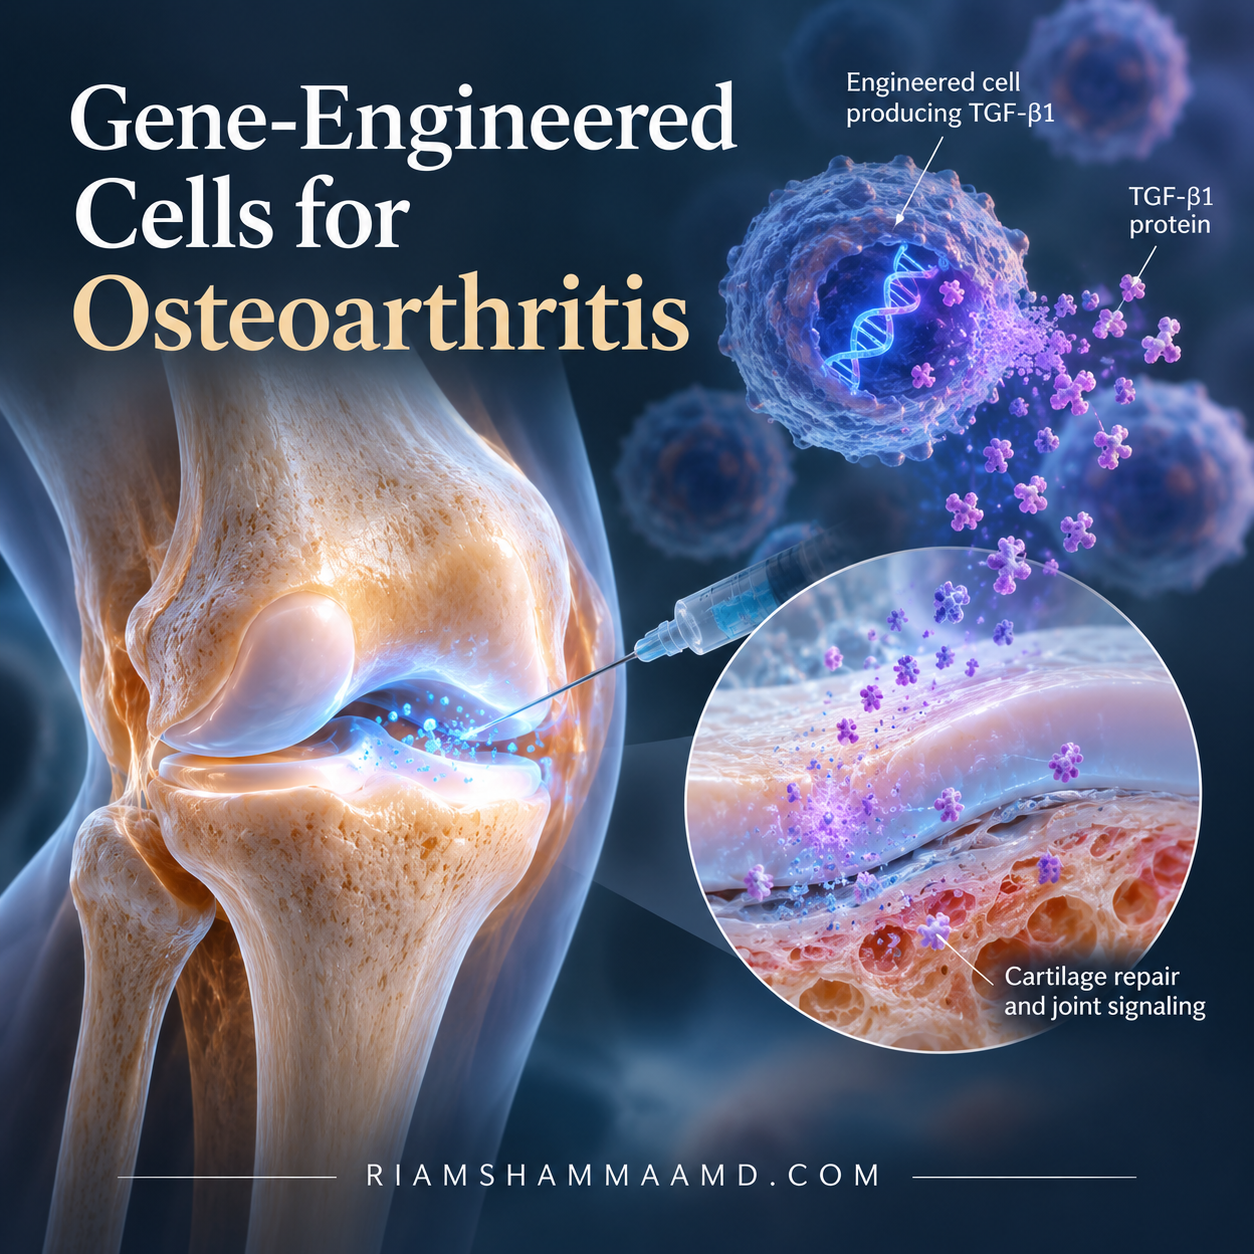
One therapy currently in Phase III uses cartilage cells (chondrocytes) together with genetically modified cells that produce TGF-β1, a protein involved in cartilage homeostasis and repair. In effect, the cells become a local biological delivery system, producing the therapeutic signal directly inside the joint.
The clinical results so far have been mixed.
The first US Phase III trial, reported in July 2026 and involving 531 patients with knee osteoarthritis, did not significantly outperform saline for pain or function at 12 months. We are still waiting for the results of the second Phase III trial.
I don't think the negative result makes the approach any less interesting scientifically. If anything, it raises important questions about which is the most important protein being expressed for repair, whether a different engineered signal—or combination of signals—could produce a better result.
Rather than depending entirely on the natural regenerative properties of MSCs or other cells, we can potentially engineer cells to express specific growth and healing factors, anti-inflammatory molecules, chemokines, or other proteins depending on what we are trying to accomplish.
For osteoarthritis, that opens an entirely new area of research: not simply finding the right cell, but learning how to make that cell more effective.